
Getting care
Can video consultations diagnose ear infections?
It depends where the infection is. An outer ear infection can often be recognised on a call. A middle ear infection cannot, and knowing which you have is the useful part.
The short answer
It depends where the infection is. A doctor can often suspect an outer ear infection on a video call, because the signs are external: pain when you pull your earlobe or press the small bump in front of your ear, and redness or swelling at the opening of the ear canal. Even then the ear canal may still need examining, partly because some ear drops can damage the inner ear if the eardrum has a hole in it, so they are only used when the eardrum is intact. A middle ear infection cannot be confirmed remotely, because that means inspecting the eardrum with an otoscope, and no phone camera can do that. What the call gives you either way is a plan: treatment you can start, or a clear reason to be seen in person and what to ask for when you are.
Worth knowing
- An outer ear infection, often called swimmer's ear, affects the ear canal and can often be assessed on a video call.
- A middle ear infection sits behind the eardrum. Confirming it needs an otoscope, which is a physical instrument, so it cannot be settled on a call.
- You cannot reliably tell the two apart yourself, which is the reason to ask rather than to guess.
- Ear infections often clear up on their own within about three days, and antibiotics are no longer routinely used for ear infections in children.
- The outcome of the call is a plan: what to do now, what would change it, and whether you need to be seen.
In this guide
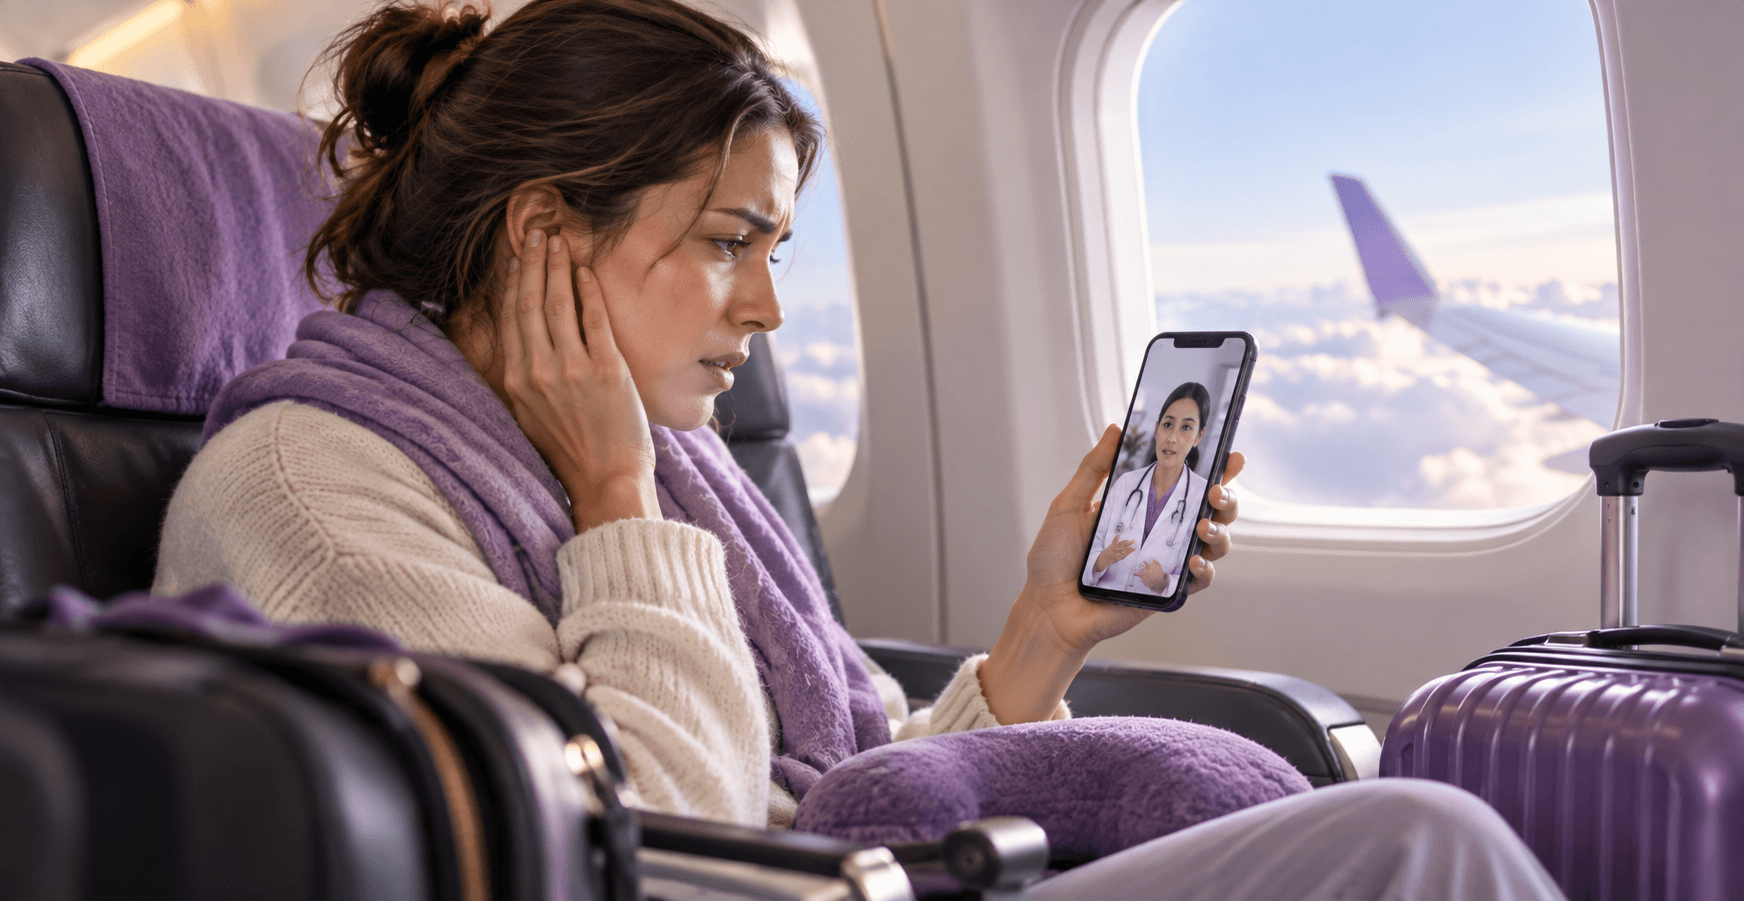
An earache is one of the most disruptive things to go wrong on a trip. A throbbing, persistent ache can take out a day at the beach, make a city you saved for miserable to walk around, and turn the flight home into something you are dreading rather than looking forward to.
So you are sitting in your hotel room with a hand over your ear, wondering whether this is worth finding a clinic for. Can a doctor work this out over a video call?
The answer depends on where the infection is. Some ear infections can be assessed on video and some cannot, and the difference is anatomical rather than a matter of how good the connection is. This article explains which is which, and what you get from the call in either case.
One thing worth setting out first. A doctor can assess your symptoms and advise on the appropriate next steps, and they can judge how likely an ear infection is and which type it looks like. In some cases an in person examination is still needed for a definitive diagnosis, and this article is largely about why.
Not all ear infections are the same
To understand what a camera can and cannot show, you need the two types that most often catch travellers out. They are named for where they sit.
Outer ear infection, or swimmer's ear
This one affects the ear canal, the tube between the outer ear and the eardrum. It is commonly set off by something irritating that canal: water after swimming, earplugs, eczema, or a bacterial or fungal infection. Its formal name is otitis externa, and it can be intensely painful for something so shallow.
It affects adults and children alike, which is part of why it turns up so often in a holiday context. A week of swimming is a week of water in the ear canal.
Middle ear infection, or otitis media
This one sits in the space behind the eardrum, and it is usually linked to a cold or flu, where fluid builds up and becomes infected. It is the type that most often affects children, though adults get it too.
The two are not alike in what causes them. Acute diffuse otitis externa, the swimmer's ear kind, is usually bacterial according to the MSD Manual, with fungal infection a less common cause. That matters later: it is the reason antibiotics are not the automatic answer to an earache, and the reason the two are not treated the same way. Most ear infections clear up within about three days, though symptoms sometimes last up to a week.
What can a doctor actually assess on a video call?
More than you would expect for one of them, and nothing at all for the other. Here is where the line falls.
Often assessable: the outer ear
An outer ear infection can often be assessed remotely, because its telling signs are on the outside. During the call the doctor will usually ask you to do two things:
- Gently pull on your earlobe.
- Press on the small, firm bump just in front of the ear canal, called the tragus.
If either of those is significantly painful, that points towards the outer ear. They will also use your camera to look for redness and swelling at the opening of the canal, which is visible from outside in a way that nothing behind the eardrum is.
The hard limit: the middle ear
This is where a video call runs out of road, and it is worth being precise about why. Confirming a middle ear infection means looking through the eardrum for fluid, inflammation or bulging behind it. That is done with an otoscope: the handheld instrument with a small light and a magnifying glass that a doctor puts to your ear during an in person examination.
A phone or laptop camera cannot show a clinician the eardrum. No lighting, no resolution and no angle changes that, so this is a limit of physics rather than of telemedicine.
The analogy the writer of this piece uses is a good one. Trying to diagnose a middle ear infection by camera is like trying to tell whether a room is untidy by looking at the outside of a closed frosted door. You need to open the door, and the otoscope is the door.
Why the call is still the right first step
If half of the answer is that a doctor may not be able to confirm it, the obvious question is what you are getting. You are getting the plan, which is the part that is genuinely hard to work out alone in a country whose health system you do not know.
Depending on what the assessment shows, that plan is usually one of three things.
- It looks like an outer ear infectionTreatment for this is often eardrops rather than tablets, and the options include antibiotic, antifungal, steroid and painkilling drops depending on the cause. Your doctor may issue one when it’s clinically appropriate and local rules permit. Where a prescription is not the answer, the doctor can tell you what to ask a local pharmacist for.
- It looks like a middle ear infectionThe plan is a recommendation to be seen locally for an otoscope examination, and the useful part is that you go knowing what you are going for. Walking into an unfamiliar clinic able to say what has been assessed and what needs looking at is a different experience from walking in and starting from your symptoms in a language you do not speak.
- Either way, pain and safetyThe doctor can advise on managing the pain in the meantime, and on the symptoms that would mean stopping the plan and being seen urgently instead. That second half is the one people underestimate, and it is the reason not to wait it out on a search result.
It is also worth knowing when an earache is ordinarily worth a doctor at all. Ear infections often get better on their own within three days. The signs that it needs looking at are an earache that is not improving after three days, a child under twelve months you think has one, or ear infections that keep coming back. NHS says to get urgent advice (an urgent GP appointment or NHS 111 in the UK) for ear infection symptoms with any of these: feeling generally unwell, a very high temperature or feeling hot, cold or shivery, swelling around the ear, fluid coming out of the ear, a change in hearing or new hearing loss, being sick, dizziness or a severe sore throat, a child under 12 months with earache in both ears, diabetes or a heart, lung, kidney or neurological condition, or a weakened immune system. NHS mastoiditis guidance adds pain, redness or swelling behind the ear, which can make the ear stick out, as a reason for urgent advice. Weakness or drooping on one side of the face is different: NHS lists face weakness on one side as a stroke symptom, and says to call 999 if you think it could be a stroke; abroad, call the local emergency number. If you are already at that point, seeing a doctor about an ear infection while travelling is the practical next step.
Why you will not always be handed antibiotics
Because a middle ear infection is often viral, and antibiotics do nothing for a virus. They are no longer routinely used for ear infections in children for exactly that reason. Taking antibiotics when they are not needed also carries side effects and encourages resistant bacteria, which can make infections harder to treat in future.
So a doctor who holds off is following current guidance rather than being unhelpful, and they should tell you what would change their mind. There is more on how that decision gets made in our guide to antibiotics and video consultations.
Ear pain abroad, and what Pomodoc does about it
Pomodoc connects you with an English speaking doctor licensed to treat you in the country you are in, which is the part that decides whether a prescription is usable where you are standing and which local clinic makes sense if you need one.
What you get from the consultation is an assessment of which type of ear infection this looks like, treatment where that can be settled remotely, and a specific recommendation where it cannot. That is the honest description of the outcome: not every ear can be diagnosed down a camera, and knowing which kind you are dealing with is most of the value.
Prescriptions when local rules allow. Your doctor may issue one when it’s clinically appropriate and local rules permit. Whether it can then be dispensed depends on the country you are in.
In short
- It depends on the type. An outer ear infection, or swimmer's ear, can often be assessed on video. A middle ear infection cannot be confirmed that way.
- The otoscope is the reason. Confirming a middle ear infection means inspecting the eardrum, and that needs a physical instrument.
- The goal is a plan. Treatment you can start, or a clear recommendation to be seen and what to ask for.
- Pain can be managed either way. Advice on relief and on the red flags does not depend on confirming which type it is.
- Antibiotics are not automatic. Ear infections are often viral and often settle on their own within about three days.
Common questions
My ear really hurts. Can the doctor not just prescribe oral antibiotics?
Getting the type right comes first, because the treatments differ. An outer ear infection is often treated with eardrops rather than tablets, and antibiotics are no longer routinely used for ear infections in children at all. A doctor prescribing without knowing which one you have would be guessing, and Your doctor may issue one when it’s clinically appropriate and local rules permit.
What exactly is an otoscope?
It is the handheld instrument a doctor uses to look inside your ear: a small light and a magnifying glass in a cone that goes a little way into the ear canal. It is what lets them see the eardrum itself, which is the thing a middle ear infection sits behind.
What is the point of the call if I might end up at a clinic anyway?
You arrive at the clinic knowing what you are there for, in a language you understand, having already had the pain assessed and the urgent possibilities ruled out or not. You also find out whether you need to go at all, which for an outer ear infection you often do not. Where the line falls in general is covered in what cannot be treated with telemedicine.
Is it safe to fly with an earache?
It is worth asking before you get to the airport rather than after. Pressure changes on ascent and descent act on an ear that is already inflamed or blocked, and an ear that is merely uncomfortable on the ground can be a great deal worse in the air. A doctor can advise on managing the pressure and on whether flying is sensible for you right now, which is a much better conversation to have the day before than at the gate.
How is this different from a sore throat, where you also cannot confirm it on video?
The limitation has a different shape. With an ear, the answer splits by anatomy: one type is often assessable on camera and the other is not. With a throat, nothing is confirmable remotely without a swab, however clear the picture. Both end in a plan, but they get there differently, and the strep throat article covers that one.
Sources
- Stroke: symptomsNHSThat face weakness, with one side of the face drooping, is a stroke symptom, and that you should call 999 if you think you are having or have had a stroke.
- MastoiditisNHSThat pain, soreness, tenderness, redness or swelling behind the ear, which can make the ear stick out, are symptoms of mastoiditis and a reason to get an urgent GP appointment or help from NHS 111.
- Ear infectionsNHSThat a middle ear infection affects the space behind the eardrum and usually affects children, that an outer ear infection affects the ear canal (the tube between the outer ear and the eardrum) and is caused by something irritating that canal such as water, earplugs, eczema or a fungal or bacterial infection, that middle ear infections are caused by viruses like colds and flu, that most ear infections clear up within three days and sometimes last up to a week, that a doctor uses an otoscope (an instrument with a small light and magnifying glass) to look in the ear, that treatment may be antibiotic tablets or eardrops or antifungal, steroid or painkilling eardrops, and the three reasons to see a GP: a child under 12 months, earache not improving after three days, and repeated infections.; and the reasons to get urgent advice: feeling generally unwell, a very high temperature or feeling hot, cold or shivery, swelling around the ear, fluid coming out of the ear, a change in hearing or new hearing loss, vomiting, dizziness or a severe sore throat, a child under 12 months with earache in both ears, diabetes or a heart, lung, kidney or neurological condition, and a weakened immune system
- External otitis (acute)MSD Manual Professional VersionThat acute diffuse external otitis is usually bacterial (Pseudomonas most commonly), with fungal infection less common; and that some ear drops should not be used when the eardrum is perforated, because neomycin is ototoxic and risks inner-ear injury and permanent hearing loss through a perforation, and antifungal solutions can cause severe pain or damage the inner ear.
- AntibioticsNHSThat antibiotics do not work for viral infections, that antibiotics are no longer routinely used to treat ear infections in children, and that taking them when they are not needed can mean they will not work in future.
Keep reading
 Getting careCan video consultations diagnose strep throat?Not on its own, because confirming it takes a swab. What a doctor can judge from your throat and your symptoms, and why a likelihood plus a plan is the useful outcome.
 MedicationCan video consultations prescribe antibiotics?The honest answer is sometimes. Which infections can be judged over video, which cannot, and why a consultation that ends without a prescription has still done its job.
 Getting careWhat cannot be treated with telemedicine?Knowing what a video consultation cannot do is what makes it safe to use. The three kinds of problem that need a clinic, and the grey area where a call still helps.